

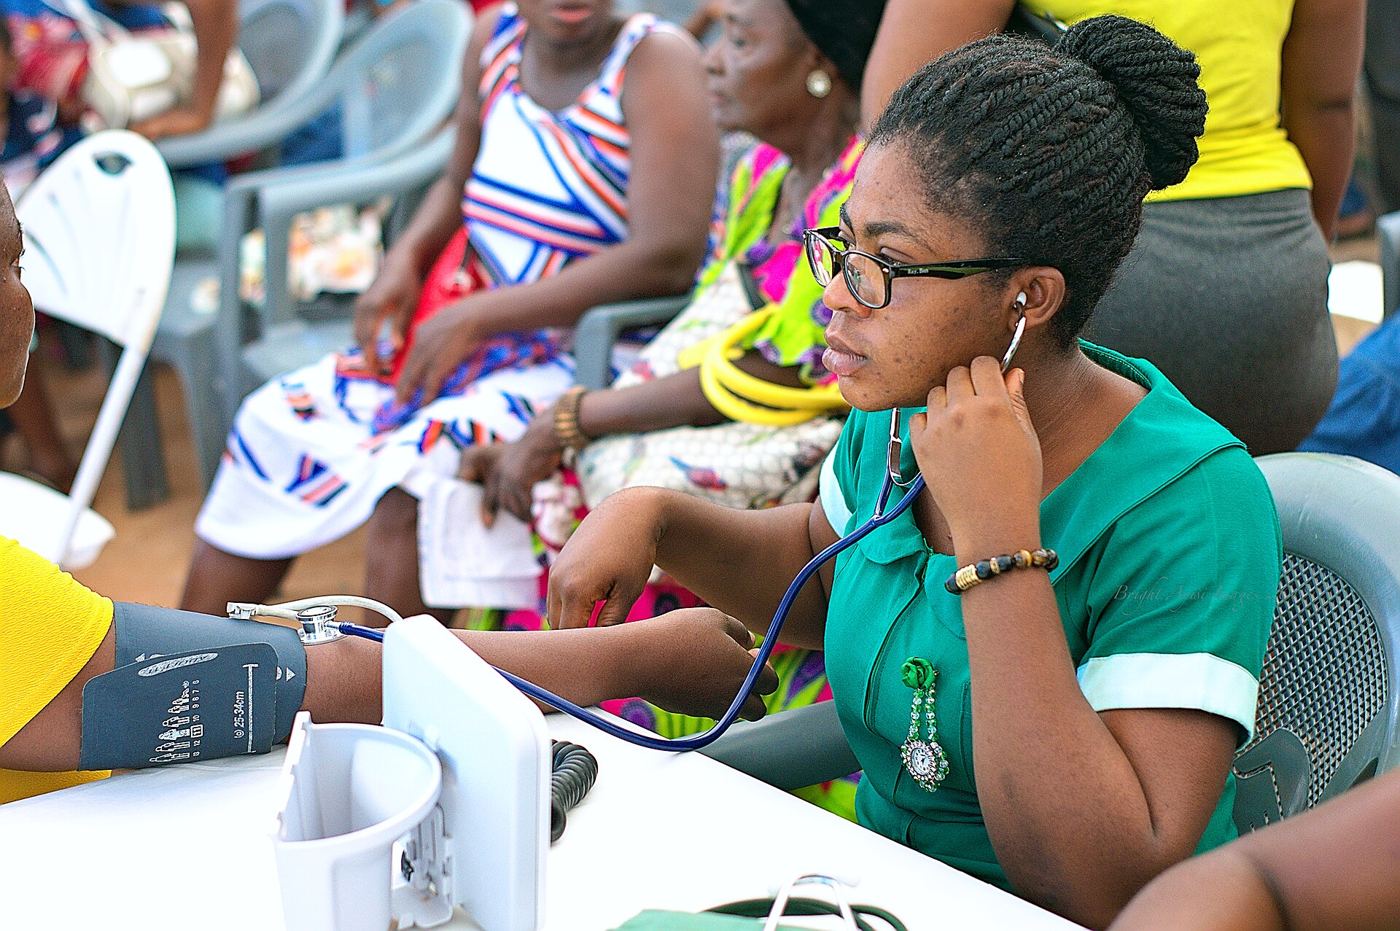
Community clinics are inviting adults for short screening appointments that check blood pressure, weight and lifestyle risks in a single visit, aiming to catch problems while they are still easy to treat. Nurses say high blood pressure in particular often produces no symptoms, so people can feel perfectly well while their risk quietly rises. The appointments take about twenty minutes and end with clear next steps rather than a leaflet and vague advice. Where results are borderline, patients are offered repeat checks instead of immediate treatment. Clinics are siting sessions in libraries and community centres as well as surgeries.
What the Evidence Shows
Health teams say the informal settings matter, because some people avoid formal medical buildings until something is wrong. Screening staff are trained to explain numbers plainly: what was measured, what range is expected and what follow-up means. Anyone found with significantly raised readings is booked promptly with a doctor, while others receive a recall date so the check becomes routine rather than one-off. Early attendance figures suggest evening and weekend sessions reach people who miss standard appointments. The programme’s value will be judged over years, in problems prevented rather than appointments completed. Reporting and analysis from sources such as World Health Organization track the same developments, and specialists following community clinic screening catching risks say the direction is now consistent across independent lines of evidence.
The Wider Context
The wider context is a health system trying to move from treating illness late to preventing it early, against budgets that reward the opposite. Evidence around community clinic screening catching risks is being weighed by guideline committees that ask two questions in order: does it work, and can ordinary services actually deliver it at scale. Many good ideas pass the first test and stall on the second.
What Happens Next
What happens next for community clinic screening catching risks depends on the slow machinery of guidelines, funding and training catching up with the evidence. Patients asking about it today should expect honest answers that include uncertainty, and clinicians say a service that explains what is not yet known earns more trust than one that oversells. The research pipeline, at least, is moving in the right direction. You can follow related developments in our coverage of health.
There is a practical lesson in all of this for readers deciding what to do today. Start with the verified facts, be wary of anyone promising certainty, and prefer reversible steps while the evidence is still developing. Circumstances differ by country, income and personal situation, so general guidance should always be weighed against your own context before you act on it in any significant or lasting way.
It is also worth remembering how quickly the picture in this area has changed before. Positions that looked settled a few years ago have been revised as new data arrived, and the same humility is appropriate now. The strongest coverage of this subject, and the most useful advice, tends to come from sources that update their views openly when the facts move, rather than defending an earlier position long after it has stopped fitting the evidence available.
